
For leaders considering a fractional CFO ambulatory surgery center engagement, the central question is not simply how many cases the center completes. It is whether the case mix, payer mix, labor model, supply spend, and operating schedule convert that volume into dependable contribution margin that supports patient access and gives care teams the time, staff, and equipment they need.
ASC growth remains a meaningful opportunity. MedPAC reported 6,436 Medicare-certified ASCs in 2024, with 3.4 million fee-for-service Medicare beneficiaries receiving ASC services. More activity does not automatically create more value. Margin matters because it helps keep caring for patients sustainable. It protects continuity and gives operators room to invest in the people and tools good care depends on.
That is why an Operations and Margin Assessment is worth doing. In four to six weeks, leadership can get a clearer view of what is actually creating margin, where access is under pressure, and which decisions are most likely to improve the day for both patients and care teams.
Volume creates opportunity. Mix determines margin.
The most useful financial view begins below total case volume. The reason to look there is not margin for its own sake. It is to understand how case mix and scheduling decisions affect patient access, delays, cancellations, and whether care teams are working in a supported, sustainable rhythm.
Every board should be able to see revenue, variable cost, and contribution margin by specialty, procedure family, and payer.
A cataract, colonoscopy, orthopedic procedure, or spine case does not contribute the same amount after supplies, implants, anesthesia, labor, and payer-specific reimbursement are included. Two surgeons may fill similar operating-room hours while producing very different results, with direct consequences for how long patients wait, whether cases are bumped or cancelled, and whether teams are rushed or properly supported.
Payer mix adds another layer. Medicare payment rates for services covered in both settings are generally lower in ASCs than in hospital outpatient departments, with MedPAC reporting that ASC rates are about 46% lower for most such services. That lower payment can still support a strong business model when the center has an efficient cost structure and a well-understood mix of commercial, Medicare, and other contracts.
The board does not need a more complicated report. It needs a more precise one. Start with contribution margin per case and contribution margin per OR hour, then review both by specialty and payer.
What a fractional CFO ambulatory surgery center review looks at first
This is the substance behind the review. A fractional CFO for an ambulatory surgery center should begin with the operating reality behind the P&L, reconciling financial results with the schedule, the preference cards, the staffing plan, and the actual payment received. These are also the measures that protect patient access and clinician capacity when volume is rising or resources are tight.
We would look first at five connected areas:
Case mix
Which procedures are growing, which are declining, and which generate the strongest margin after direct costs?Payer mix
What share of cases and revenue comes from each payer, and how does allowed revenue compare across similar procedures?Labor cost
Are staffing hours aligned with cases on the schedule, or is the center paying for excess capacity, overtime, agency coverage, or inefficient shift patterns?Supply and implant cost
Are high-cost items being tracked by procedure and physician, with purchasing variation visible to leadership?Throughput
Are cancellations, turnover time, late starts, extended recovery, or unused block time limiting the value of available capacity?
This review is not about reducing care to a spreadsheet. It is about giving operators a clearer view of where capacity and clinical effort are creating value. A strong scorecard helps the board support better decisions about service lines, physician recruitment, block allocation, staffing, and payer strategy.
MedPAC also notes that ASC costs are not well understood nationally because Medicare does not require ASCs to submit cost data. That makes internal cost visibility especially important. A center should not wait for a national benchmark to tell it whether a particular procedure is working economically.
Labor and supplies are where busy centers lose clarity
Labor is often the largest controllable operating expense, but the relevant question is whether labor hours follow the work. Care teams are not a cost line to squeeze. Staffing decisions should support safe, well-paced care, with resources matched to the work so teams are supported rather than stretched.
Review productive hours per case, overtime, agency use, and staffing by day of week against scheduled cases, acuity, and turnover. Supply cost deserves the same discipline. Device-intensive specialties can produce attractive revenue while creating narrow margins, so operators should review supply cost by CPT family or procedure group, with physician preference variation visible, rather than rely on a blended monthly ratio that can hide where margin is actually being made or lost.
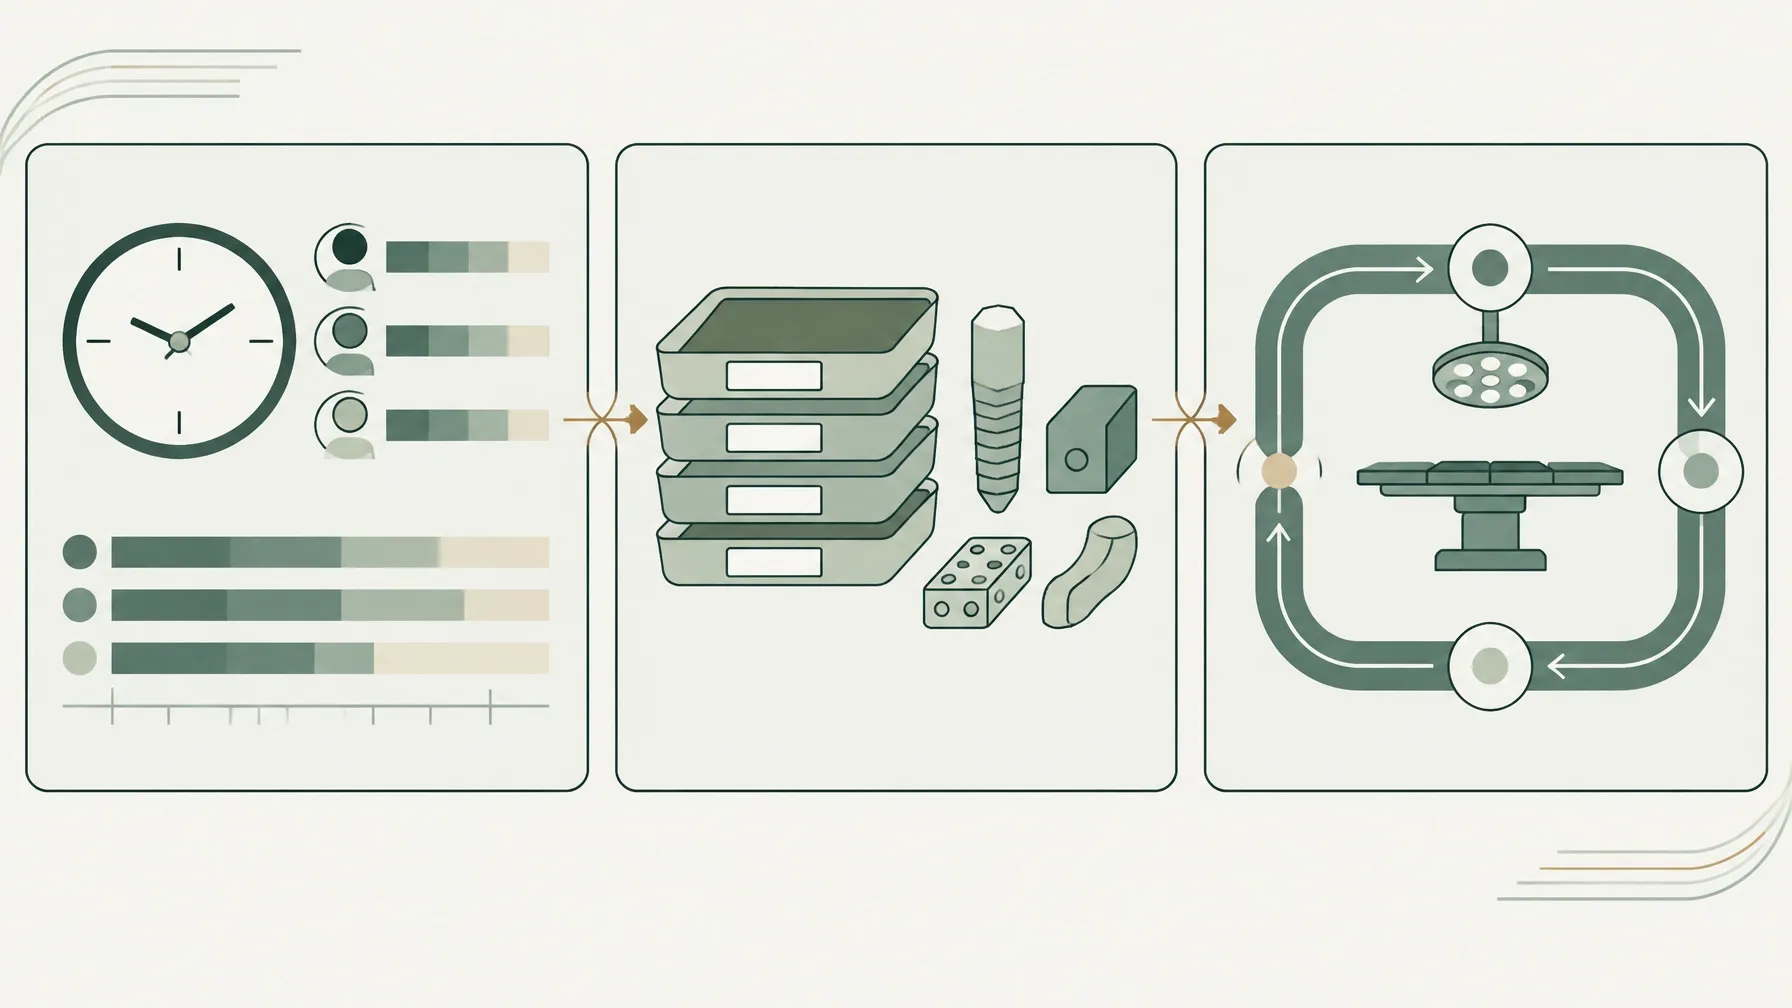
The practical goal is not to impose a single cost target on every specialty. It is to understand the economic shape of each service line and establish ownership for the factors operators can influence.
The monthly ASC board scorecard
A board scorecard should be short enough to use in the meeting and detailed enough to prompt a decision. We recommend organizing it around four views.
1. Volume and capacity
- Cases completed, month and year to date
- Cases by specialty, procedure group, and surgeon
- OR utilization, measured against staffed or available hours
- Block utilization and released block time
- Same-day cancellation and no-show rate
2. Revenue and mix
- Net revenue per case by specialty
- Net revenue per OR hour
- Payer mix by cases and revenue
- Allowed amount by payer and procedure group
- Revenue-cycle performance, including denials, collections, and receivables
- Contribution margin by specialty and payer
3. Cost and productivity
- Labor cost as a percentage of revenue
- Labor hours per case
- Overtime, agency, and premium labor
- Supply and implant cost per case
- Supply cost by procedure group and surgeon
4. Quality and operating reliability
- Unplanned transfers or hospital visits
- Patient experience indicators
- First-case on-time starts
- Cancellations tied to authorization, staffing, equipment, or patient readiness
The point is not to turn the board into an operating committee. The point is to make the economic drivers visible early enough for the board and management team to act together.
The first margin question to ask this quarter
Ask this: Which procedure and payer combinations are using the most OR capacity without producing an acceptable contribution margin?
That question is more useful than asking whether volume is up or down. It connects demand, reimbursement, cost, and capacity in one view. It also creates a practical path forward: renegotiate a contract, change a supply protocol, adjust staffing, reassign block time, recruit a different physician profile, or reconsider how a service line is structured, all with the aim of protecting access, reducing cancellations, and giving care teams a more predictable day.
The answer should be based on actual net revenue and direct cost, not gross charges or a generalized margin assumption. It should also be reviewed with clinical and operational leaders, because the best decision may involve redesigning the workflow rather than removing the case type.
For new sites, expansions, or major service-line decisions, the same discipline belongs in the planning phase. An ASC feasibility study consultant should make demand, payer mix, physician alignment, operating assumptions, and pro forma economics explicit before a capital decision is made. Our ASC Feasibility and Market Study is structured around those questions.
Why the numbers matter to patients and care teams
A financially healthy center is more likely to keep its doors open, invest in equipment and staff, recruit the physicians patients need, expand access, and avoid the instability that disrupts continuity of care.
That is why financial performance and patient experience belong in the same conversation. When the economics are understood and managed well, leaders have more room to support reliable schedules, steadier staffing, and a better day for both patients and the teams caring for them.
Where to start
Pull the last twelve months of cases, net revenue, payer mix, labor cost, supply cost, cancellations, and OR utilization. Map them by specialty, procedure group, and payer. Then select the three combinations with the greatest volume and review their contribution margin per case and per OR hour.
That exercise will usually show whether the next opportunity is more volume, better mix, lower cost, or better throughput. The answer may be different by service line, which is why a single center-wide margin percentage is not enough. Review the findings with clinical and operational leaders, including care team input, so the decisions reflect what is actually happening for patients and staff.
If your ASC is busy and you want a clearer view of what is creating margin, start a conversation with BreckenReese Ventures. We can help you decide whether a focused review, including an operations and margin assessment, is the right next step.
Source: MedPAC, "Ambulatory surgical center services: Status report," Chapter 11, March 2026 Report to the Congress.